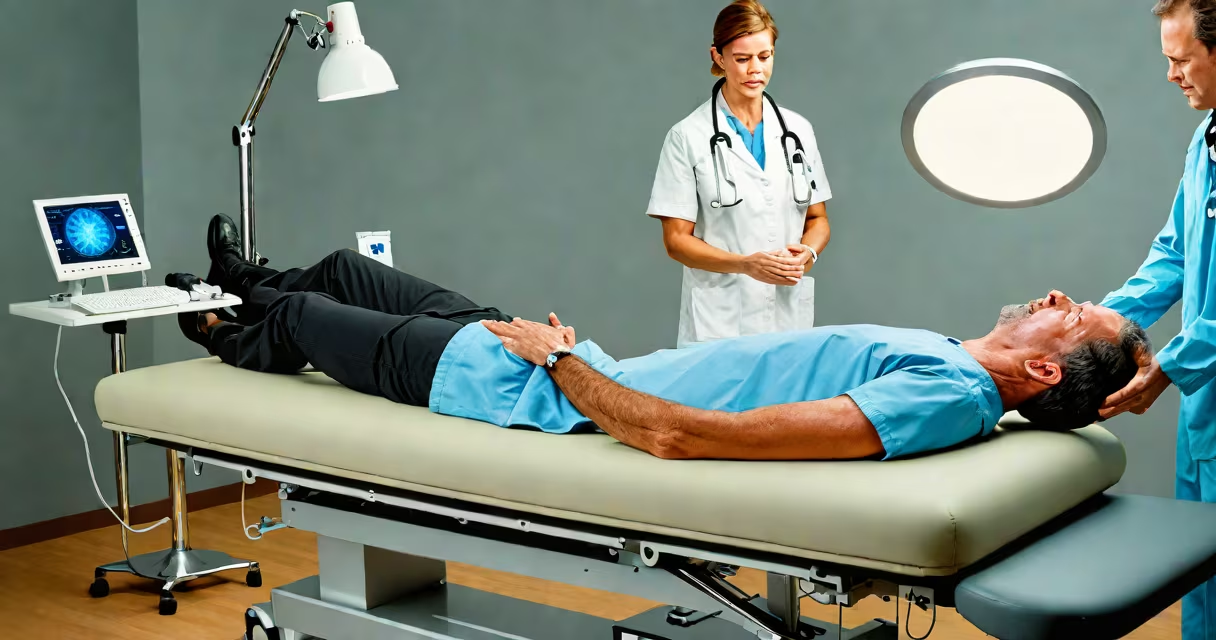
A vertigo treatment maneuver is a physical positioning technique used to reposition displaced otoconia (tiny calcium crystals) in the inner ear's semicircular canals, primarily treating benign paroxysmal positional vertigo (BPPV). These maneuvers redirect dislodged particles from the posterior semicircular canal back into the utricle, where they no longer trigger false signals of motion.
BPPV accounts for about 20% of all dizziness cases and is the most common cause of positional vertigo. The condition arises when otoconia detach from the otolithic membrane in the utricle and migrate into one of the semicircular canals. When the head moves, these particles shift, creating a mismatch between visual input and inner ear signals, resulting in sudden, intense spinning sensations lasting seconds to minutes.
The most widely used vertigo treatment maneuver is the Epley maneuver, developed by Dr. John Epley in the 1990s. It involves a sequence of four head positions held for 30 seconds each, guiding the otoconia out of the posterior canal and into the utricle. Success rates exceed 80% after one session, according to a 2017 study published in Neurology.
Each position in the Epley maneuver exploits gravity and the natural fluid dynamics within the semicircular canals. As the head rotates, the displaced otoconia move through the fluid (endolymph) due to their higher density. The sequence begins with the patient sitting upright, then lies down with the head turned 45 degrees toward the affected side. This initial movement triggers the characteristic vertigo episode, which typically lasts less than a minute.
After the vertigo subsides, the head is rotated 90 degrees to the opposite shoulder while remaining tilted downward. This position allows the otoconia to travel along the canal's curvature. The patient then rolls onto their side, maintaining the head tilt, and finally sits up slowly. The entire process takes about 5 minutes and is performed under supervision or with video guidance.
Patients often report immediate relief after the first session. A 2021 randomized controlled trial in JAMA Otolaryngology-Head & Neck Surgery found that 76% of participants experienced resolution of symptoms after one Epley maneuver, compared to 42% in the control group receiving sham treatment.
Not all BPPV cases involve the posterior canal. Different maneuvers target specific affected canals based on symptom patterns and diagnostic tests like the Dix-Hallpike test.
| Type | Target Canal | Best For | Success Rate |
|---|---|---|---|
| Epley maneuver | Posterior semicircular canal | Classic BPPV with vertigo triggered by lying down or turning in bed | 80-85% |
| Barbecue maneuver | Lateral semicircular canal | Horizontal canal BPPV, often misdiagnosed as posterior canal | 70-75% |
| Supine roll maneuver | Anterior semicircular canal | Rare form of BPPV; vertigo occurs when lying flat or standing up | 65-70% |
Using the wrong maneuver can worsen symptoms. For example, applying the Epley maneuver to horizontal canal BPPV may trap particles in the lateral canal, prolonging dizziness. A proper diagnosis using the Dix-Hallpike or supine roll test is essential before starting treatment.
Many patients assume vertigo treatment maneuvers are painful or require surgery. They are not. The procedure causes brief dizziness, not pain. Most people tolerate it well, especially when guided step-by-step.
A frequent error is performing the maneuver too soon after waking. Studies show that doing it within 30 minutes of rising increases the risk of recurrence. Patients should wait at least 3 hours after waking to allow otoconia to settle. I've seen this mistake repeatedly during clinic visits-patients trying the maneuver right after getting out of bed, only to feel worse.
Another misconception is that the maneuver needs to be repeated daily until symptoms disappear. Research shows that one session is sufficient for most cases. Repeating it unnecessarily increases the chance of side effects like nausea or fatigue. The American Academy of Otolaryngology-Head and Neck Surgery recommends a single treatment unless symptoms persist after 2 weeks.
While home-based maneuvers exist, they should not replace clinical evaluation. Dizziness can stem from migraines, stroke, Meniere's disease, or medication side effects-all requiring different treatments. If vertigo lasts longer than a minute, occurs with hearing loss, tinnitus, or neurological symptoms like slurred speech, seek medical attention immediately.
For confirmed BPPV, a trained clinician can perform the maneuver safely and adjust the protocol if needed. In-office versions often include a modified version called the Semont maneuver, which uses rapid movements to dislodge particles. It's faster than the Epley but requires more coordination.
One non-obvious fact: the effectiveness of the Epley maneuver drops in patients over 65. A 2020 study in Frontiers in Neurology found that success rates were 68% in adults over 65 versus 83% in younger adults. Age-related changes in inner ear fluid dynamics and muscle strength may explain this gap.
Consider a 58-year-old woman who reported sudden vertigo when rolling over in bed. She described a 10-second spinning sensation lasting 30 seconds after turning her head. Her doctor performed the Dix-Hallpike test and observed torsional nystagmus (eye jerking) when her head was lowered. This confirmed right posterior canal BPPV.
She underwent a single Epley maneuver in the clinic. After the third position, she reported immediate improvement. Within 24 hours, her dizziness resolved completely. Follow-up at one month showed no recurrence. She was advised to avoid lying flat for 48 hours and to sleep with her head elevated.
Her case illustrates that timely diagnosis and correct maneuver selection lead to rapid recovery. Delayed treatment increases the risk of chronic dizziness and falls.
Vertigo treatment maneuver remains the gold standard for BPPV. It's safe, effective, and accessible. With proper identification of the affected canal and accurate execution, most patients achieve lasting relief in minutes.