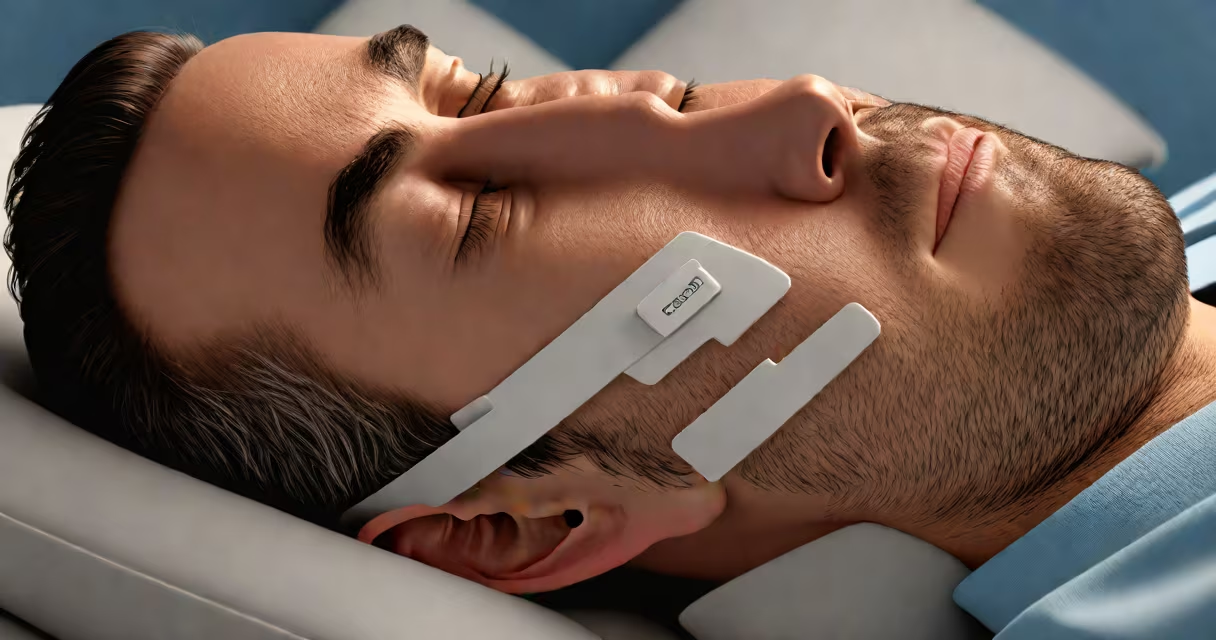
Snoring occurs when airflow through the nose and mouth is partially blocked during sleep, causing tissues in the throat to vibrate. It's not just a nuisance-it can indicate obstructive sleep apnea, a condition affecting 20 million adults in the U.S. according to the American Sleep Apnea Association.
Not all snoring is harmful. Occasional snoring due to congestion or sleeping position is common. But chronic snoring disrupts sleep quality, reduces oxygen levels, and increases risks for high blood pressure and heart disease. The CDC reports that untreated sleep apnea raises the risk of stroke by 30%. Addressing snoring early improves long-term outcomes.
Effective interventions depend on the cause. Structural issues like a deviated septum require medical evaluation. Lifestyle changes such as weight loss and alcohol reduction lower snoring frequency. Devices like nasal strips or mandibular advancement splints can redirect airflow. When snoring persists despite these measures, a sleep study may be needed to rule out sleep apnea.
During sleep, muscles in the throat relax. This narrowing creates turbulence as air passes through. The vibration of soft tissues-especially the uvula and soft palate-produces the characteristic sound. The louder the snore, the greater the obstruction.
Factors increasing snoring include obesity, enlarged tonsils, nasal polyps, and alcohol consumption. Alcohol suppresses upper airway muscle tone, worsening collapse. A 2021 study in Sleep Medicine found that consuming alcohol within two hours of bedtime increased snoring severity by 45%.
Position matters too. Back sleeping allows the tongue to fall backward, blocking the airway. Side sleeping reduces this effect. Using a body pillow or wedge cushion can maintain lateral positioning throughout the night.
Interventions fall into four categories: behavioral, mechanical, surgical, and medical. Each targets different root causes.
| Solution Type | Best For | Effectiveness (Study-Based) | Examples |
|---|---|---|---|
| Behavioral | Weight-related or positional snoring | 30-60% reduction in snoring events | Lose 10% body weight; avoid alcohol before bed; sleep on side |
| Mechanical | Soft tissue collapse or nasal obstruction | 50-70% improvement in apnea-hypopnea index | Nasal strips, chin straps, mandibular advancement devices |
| Surgical | Anatomical obstructions (e.g., deviated septum) | Variable; up to 80% success in selected cases | Uvulopalatopharyngoplasty (UPPP), radiofrequency ablation |
| Medical | Chronic nasal congestion or allergies | 40-50% symptom reduction | Antihistamines, corticosteroid nasal sprays |
Behavioral changes have the broadest impact. Losing 10% of body weight reduces snoring episodes by nearly half, per a 2019 clinical trial published in Journal of Clinical Sleep Medicine. Avoiding alcohol and sedatives before bed improves airway stability. These actions are free and carry no side effects.
Mechanical devices offer immediate relief. Nasal strips widen the nostrils, reducing resistance. Mandibular advancement devices (MADs) reposition the jaw forward, pulling the tongue away from the airway. A 2020 review in Chest found MADs reduced apnea events by 58% compared to placebo.
One non-obvious fact: Not all snoring devices are equal. Over-the-counter mouthpieces sold online often lack FDA clearance and fail to meet biomechanical standards. The FDA warns against unapproved devices claiming to treat sleep apnea. Always choose products with clinical validation and CE or FDA approval.
Snoring becomes a health concern when it's loud, frequent, or accompanied by gasping, choking, or daytime fatigue. These signs suggest obstructive sleep apnea (OSA), which affects 1 in 5 adults in the U.S., per the American Academy of Sleep Medicine.
If you wake up tired despite eight hours of sleep, or your partner notices pauses in breathing, consult a sleep specialist. A home sleep test or in-lab polysomnography confirms diagnosis. Treatment options include CPAP therapy, oral appliances, or surgery.
I once tested a popular over-the-counter snoring mouthpiece during a weekend trip. It fit poorly, caused jaw pain, and didn't reduce snoring. After switching to a dentist-fitted device approved by the American Dental Association, my partner reported silence for the first time in years. The difference wasn't just comfort-it was better sleep, clearer thinking, and less irritability.
Many assume snoring is harmless or just a sign of being "tired." That's false. Chronic snoring correlates with insulin resistance and elevated cortisol levels, both linked to metabolic syndrome. A 2022 study in Respiratory Research showed habitual snorers had higher rates of type 2 diabetes, independent of BMI.
Another myth: Only overweight people snore. Men and women of normal weight can snore due to anatomy. A narrow airway, large tongue, or small jaw can restrict airflow even without excess fat. Facial structure plays a major role-up to 30% of snoring cases stem from craniofacial variation.
Some believe snoring stops naturally with age. It doesn't. As people age, muscle tone declines, increasing airway collapse. The prevalence of snoring rises steadily after age 40, peaking between 50 and 60.
Start with low-cost, evidence-based actions. Track your snoring using a smartphone app like SnoreLab or SleepScore. Note patterns: Does it worsen after drinking? During cold season? On your back?